Quick answer
Not every leaky mitral valve needs a procedure. Mild leaks are often monitored. Severe leaks may need surgery or a clip, depending on symptoms, heart size and pumping, the cause of the leak, and your surgical risk.
In this article
- What a leaky mitral valve means
- The most important question: primary or secondary?
- How the leak is assessed
- When monitoring may be enough
- When severe primary regurgitation needs treatment
- What is MitraClip?
- Does a clip help in secondary regurgitation?
- Surgery or clip?
- Questions to ask your cardiologist
- Frequently asked questions
- Practical takeaway
You feel fine, but your echo report says “mitral regurgitation”. Or you have become breathless climbing stairs, and someone mentions a clip procedure. Does every leak need fixing? No. The right decision depends on how severe the leak is, why it happened, and what it is doing to your heart.
What a leaky mitral valve means
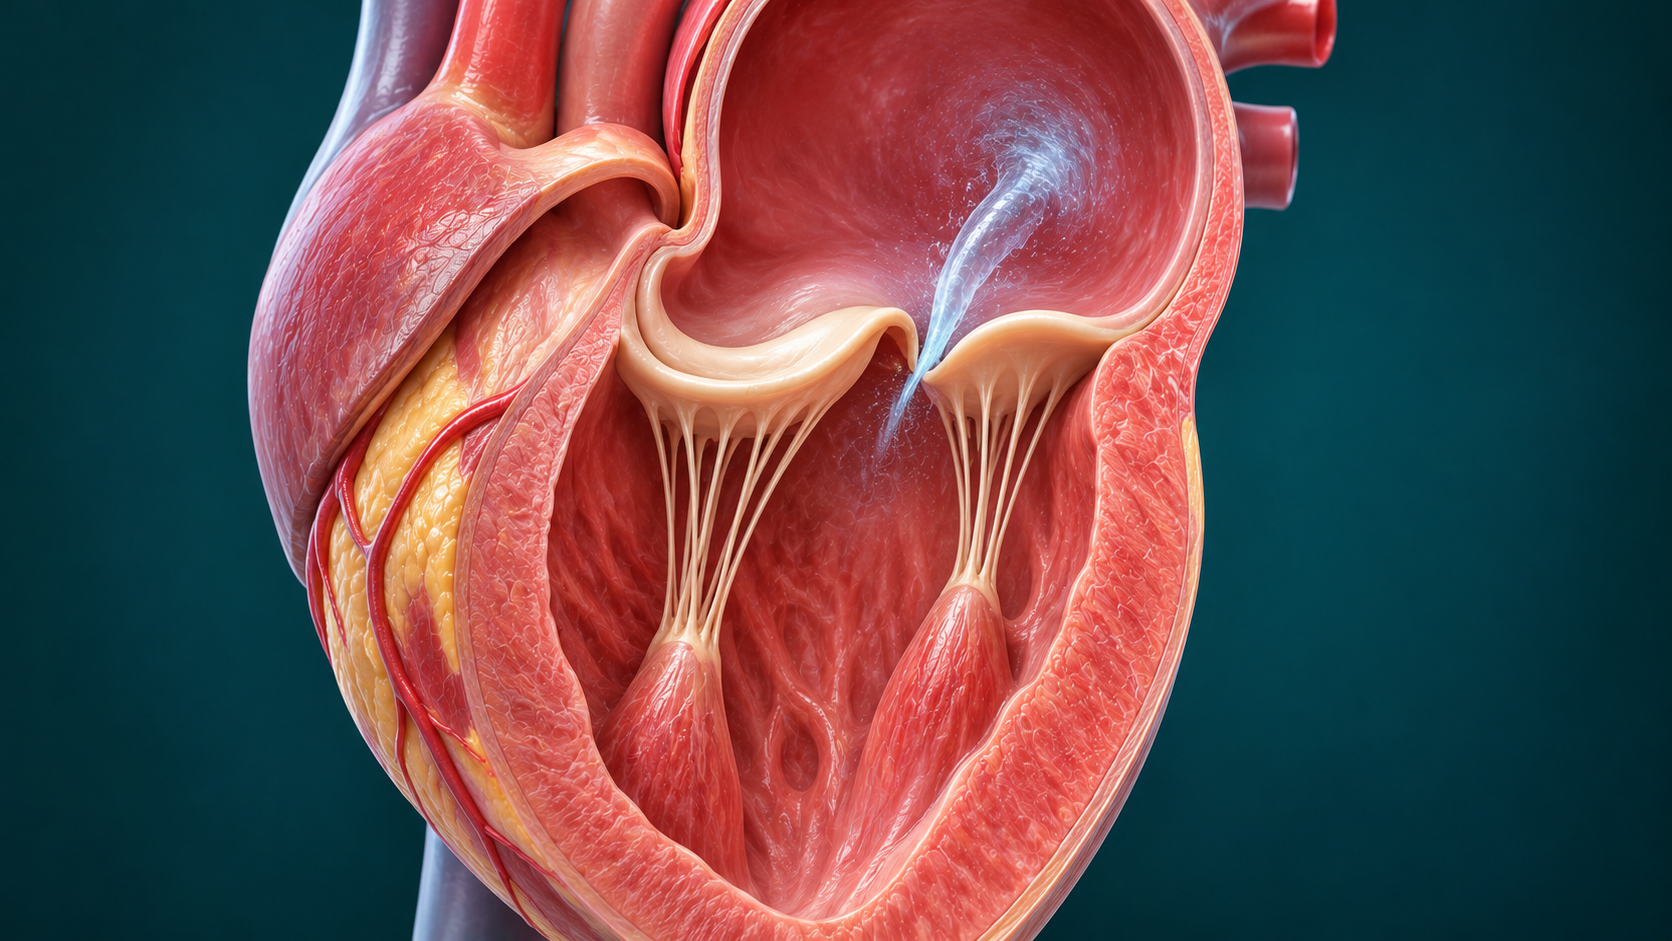
The mitral valve sits between the heart’s left upper chamber (left atrium) and left lower chamber (left ventricle). When the ventricle pumps, the valve should close so blood moves forward to the body. If it does not seal, some blood leaks backward. Doctors call this mitral regurgitation.
Over time, a significant leak can make the heart work harder. Some people notice breathlessness, tiredness, reduced exercise capacity, leg swelling or palpitations. Others have no symptoms, even when the leak is significant.
The most important question: primary or secondary?
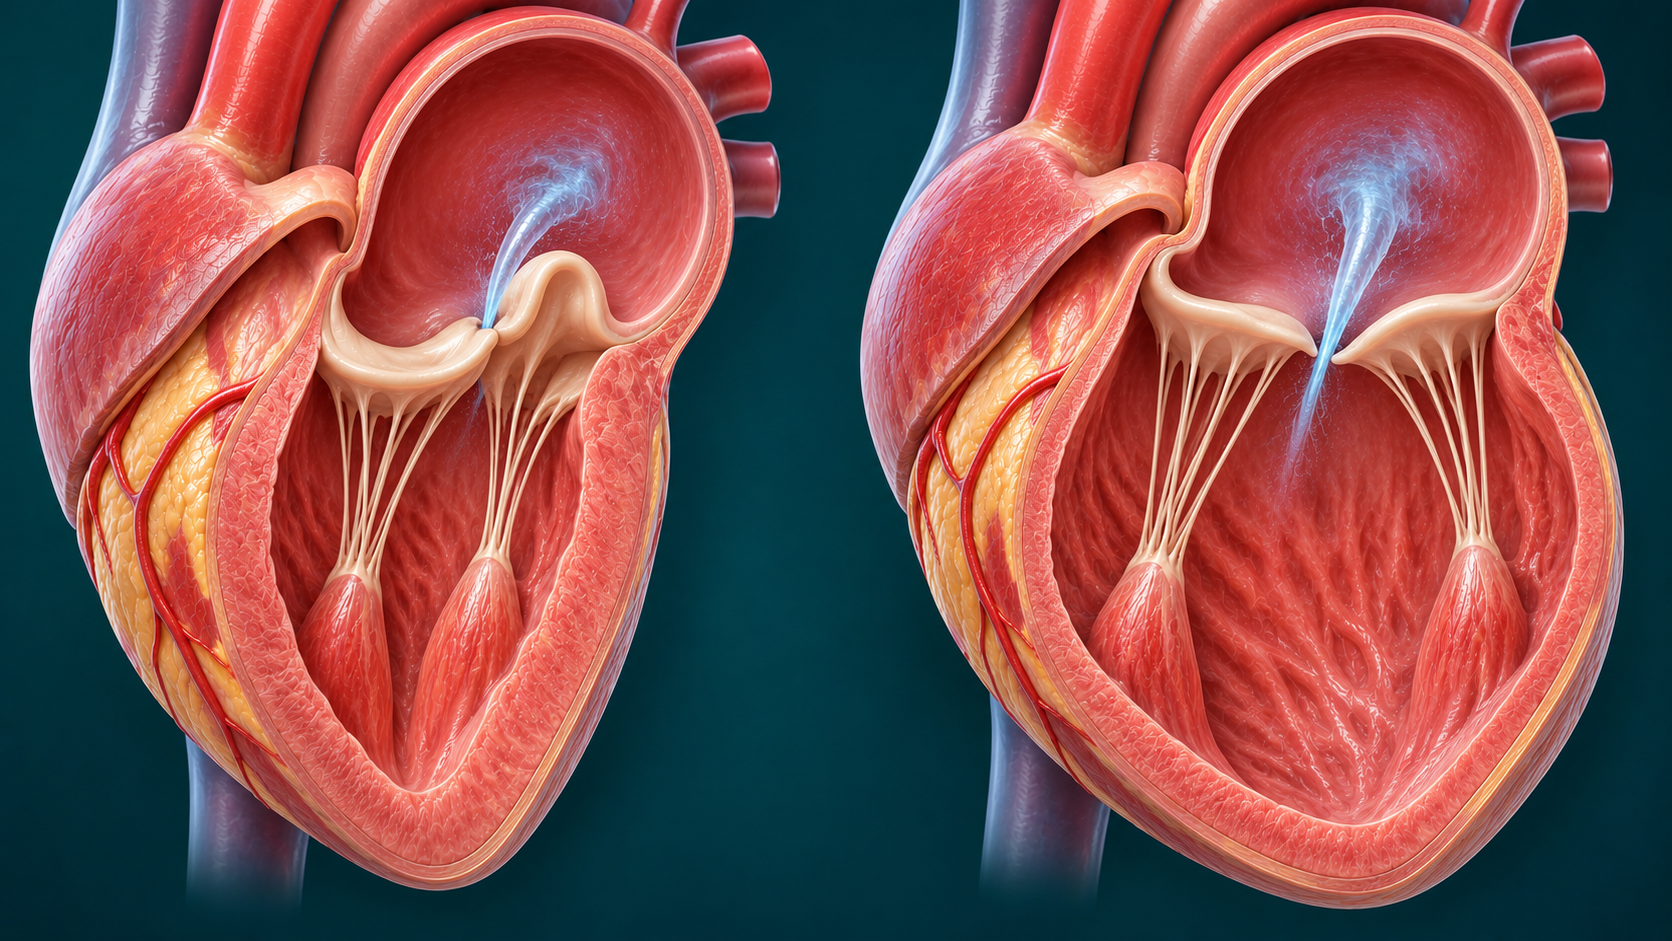
Primary mitral regurgitation
Here, the valve itself is the problem. A common example is degenerative valve disease, in which the valve structure is abnormal. Fixing the valve treats the underlying mechanical problem.
Secondary mitral regurgitation
Here, the valve may be structurally normal, but a weak or enlarged heart prevents it from closing. This is often linked to left ventricular remodelling, coronary disease, cardiomyopathy or atrial enlargement. Treating heart failure and other causes comes first, because the valve is only part of the problem.
Rheumatic valve disease is a different cause that needs its own assessment, so ask your cardiologist if you have a history of rheumatic fever.
How the leak is assessed
An echocardiogram is the key test. Your cardiologist will not rely only on the words “mild”, “moderate” or “severe”. They will also look at the valve’s structure, heart chamber size, pumping function and lung pressures. Additional imaging may be needed to plan treatment.
When monitoring may be enough
A mild leak with a normal-sized heart and no symptoms often needs follow-up rather than a procedure. Your cardiologist should set the schedule. Report new breathlessness, swelling or reduced stamina rather than waiting for your next visit.
When severe primary regurgitation needs treatment
Symptoms are a major trigger. US guidance recommends mitral surgery for symptomatic severe primary regurgitation when the ejection fraction is above 30%.
Patients without symptoms may also need treatment. Surgery is recommended when tests show early heart strain, such as ejection fraction at or below 60%, or end-systolic diameter of 40 mm or more. The goal is to act before permanent damage develops. Repair is generally preferred over replacement for degenerative disease when possible.
The 2025 European guideline keeps surgical repair as the preferred treatment for severe primary regurgitation. It reserves transcatheter edge-to-edge repair for patients who are inoperable or high risk, as judged by a Heart Team.
What is MitraClip?
MitraClip is one type of transcatheter edge-to-edge repair. A catheter is guided through a vein in the leg to the heart, and a clip joins parts of the valve leaflets to reduce the leak. Imaging guides the placement. The chest is not opened, but it is still a major heart procedure with its own risks, and anatomy may not be suitable for everyone. Read more about MitraClip.
Does a clip help in secondary regurgitation?
The evidence is real, but it does not apply to everyone.
- COAPT found that adding MitraClip to medical therapy reduced heart failure hospitalization and death.
- MITRA-FR showed no significant difference compared with medical therapy alone.
- RESHAPE-HF2 enrolled 505 patients and found fewer heart failure hospitalizations and deaths at 2 years with the clip plus medicines.
Doctors believe patient selection matters, particularly how severe the leak is compared with the size of the ventricle. Experts still debate how far these results settle the question. In the trials, the clip was added to medicines, not used instead of them.
Surgery or clip?
| Question | Surgery | Transcatheter clip |
|---|---|---|
| Main use | Preferred for many suitable patients with severe primary disease | High-risk or inoperable patients, and selected secondary disease |
| Access | Surgical | Catheter through a leg vein |
| Key consideration | Surgical risk and likelihood of durable repair | Valve anatomy and patient selection |
A Heart Team that includes cardiologists and surgeons is best placed to compare these options for you.
Questions to ask your cardiologist
- Is my leak primary or secondary?
- How severe is it, and how is it affecting my heart size and pumping?
- Are my medicines fully optimized?
- Is repair possible, or would I need replacement?
- Is my valve anatomy suitable for a clip?
- What are my risks with each option, and with waiting?
Frequently asked questions
Can a leaky mitral valve heal by itself?
A structurally damaged valve does not usually repair itself. Secondary leaks are different, because they depend on the heart around the valve. They may change as heart function and heart failure treatment change, so repeat echo tests can be useful.
How often will I need an echo?
It depends on how severe the leak is, your symptoms and how your heart is coping. Your cardiologist will set the schedule. Keep your earlier reports, because comparing them over time can show changes that one test cannot.
Can I exercise with a leaky valve?
That depends on severity, symptoms and heart function. Many people can stay active, but the safe level differs from person to person. Ask your cardiologist for specific advice, particularly before heavy exercise or competitive sport.
Do medicines fix the leak?
Medicines do not repair a damaged valve. They are still central to treating heart failure and related conditions, and can matter greatly in secondary disease. In the clip trials, the procedure was added to medicines rather than replacing them.
Is MitraClip safer than surgery?
It avoids opening the chest, but that does not make it the better choice for everyone. Surgical repair remains preferred for many suitable patients with severe primary disease. The right option depends on your valve anatomy, overall health and procedure risks.
Am I too old for treatment?
Age alone does not answer the question. Your overall health, valve anatomy, symptoms and treatment risks all count. A Heart Team assessment can explain which options are realistic for you.
When should I seek urgent care?
Seek urgent care for severe breathlessness, fainting or chest pain. Contact your cardiologist soon if you notice new leg swelling, palpitations, or find everyday activity harder than before.
Practical takeaway
A leaky mitral valve is not automatically dangerous, and it should not be ignored. Keep your echo reports, attend follow-up and report new symptoms. Seek urgent care for severe breathlessness, fainting or chest pain. If heart failure is part of your diagnosis, read our heart failure guide.